
 TR
 EN

ABSTRACT
Objective
Although splenic abscess is rare in children, it carries a significant risk of morbidity and mortality. When combined with appropriate antimicrobial therapy, percutaneous aspiration may be preferred as an alternative to splenectomy. This case presents a splenic abscess caused by Salmonella enterica in a immunocompetent pediatric patient, along with concurrent Brugada syndrome. We report the case of a 14-year-old immunocompetent patient who developed a splenic abscess caused by S. enterica concurrently with Brugada syndrome. The patient presented with complaints of palpitations and seizures. On examination, fever, tachycardia, and splenomegaly were noted. Laboratory tests revealed thrombocytopenia, lymphopenia, as well as increased C-reactive protein, and N-terminus pro-B-type natriuretic peptide. While echocardiogram was normal, but the electrocardiogram revealed a Brugada pattern. Imaging studies performed to investigate the etiology of fever revealed an abscess in the spleen. The abscess was drained percutaneously, and S. enterica was identified as the causative agent. Ciprofloxacin treatment was given for ten weeks. The abscess completely resolved on follow-up ultrasonography. This case demonstrates that a rare Salmonella -induced splenic abscess in an immunocompetent pediatric patient can be successfully treated with percutaneous drainage and antibiotic therapy
KEYWORDS
Splenic abscess, Salmonella enterica, percutaneous drainage
INTRODUCTION
Splenic abscesses, which are relatively rare, are most commonly caused by bacteremia originating from various infection sites. Risk groups include immunosuppressed individuals, those with hemoglobinopathies, and diabetes patients. Immunodeficiency associated with the human immunodeficiency virus (HIV) is another risk factor. Large-scale studies have shown that 33-63% of patients with splenic abscesses are immunosuppressed (1-3). The leading causes of splenic abscesses include streptococci, staphylococci, Salmonella spp., Escherichia coli, and Klebsiella pneumoniae (1,4). However, with the increasing number of immunosuppressed patients, recent publications have also reported an increased number of fungal isolates, including Candida spp., Aspergillus spp., and Mucorales spp. In patients with HIV infection, Salmonella spp. and Mycobacterium tuberculosis are common causes of splenic abscesses (5). Non-typhoidal Salmonella (NTS) is a leading cause of invasive disease associated with bacteremia in sub-Saharan Africa. In this population, invasive NTS infections predominantly affect adults with HIV infection and young children. In contrast, in high-income countries, invasive disease is largely restricted to young children, the elderly, individuals with chronic illnesses, and those with immunodeficiencies (6). Diagnosis can be easily made using clinical findings along with computed tomography (CT) and abdominal ultrasonography (US). Management of the abscess involves antibiotic treatment combined with percutaneous aspiration or splenectomy. Recent data show successful treatment and high survival rates with antibiotics alone, without the need for splenectomy (7,8). Brugada syndrome (BrS) is a genetic cardiac disorder characterized by a typical electrocardiographic (ECG) pattern and an increased risk of malignant polymorphic ventricular arrhythmias, which may lead to syncope or sudden cardiac death. Febrile illness has been shown to both unmask the phenotypic manifestation of BrS, and precipitate severe adverse events in patients with BrS. Pediatric patients with BrS are particularly vulnerable to serious adverse events during febrile episodes (9). In this study, we aimed to present a case of severe Salmonella splenic abscess, in which the patient initially presented with palpitations and was subsequently diagnosed with BrS. Consent and permission from the family were obtained for the case presentation.
CASE REPORT
A 14-year-old male patient was referred to our emergency department after experiencing a seizure following an initial complaint of palpitations that began the previous day. His medical history included surgery for hypospadias and a week-long hospitalization for rotavirus infection. He had no chronic diseases or regular medication use. The family history revealed that the mother had hypertension, diabetes, systemic lupus erythematosus, and autoimmune thyroiditis, while the father had autoimmune hepatitis. It was also noted that the parents were cousins. Physical examination revealed a body temperature of= 38.2 °C, pulse rate of= 128 beats/min, blood pressure of= 110/64 mmHg, and respiratory rate of= 22 breaths/min. The patient’s general condition was good, he was conscious, and he had oropharyngeal hyperemia and postnasal drip. Splenomegaly was detected during abdominal examination, and respiratory sounds were normal. Neurological examination did not reveal any pathology. On cardiovascular examination, S1 and S2 were normal and rhythmic, with tachycardia. No additional heart sounds or murmurs were detected. Laboratory tests showed a white blood cell (WBC) count of= 5.3 x 10⁹ /L [Absolute neutrophil count= 4.2 x 10⁹ /L, absolute lymphocyte count (ALC)= 0.74 x 10⁹ /L], hemoglobin= 12.6 g/dL, and platelets (PLTs)= 81 x 109 /L. Aspartate aminotransferase was= 35 U/L (0-36), alanine aminotransferase was= 35 U/L (0-31), total bilirubin was= 1.37 mg/dL (0.3-1.2), direct bilirubin was= 0.46 mg/dL (0-0.2), C-reactive protein was= 0.14 g/L (0-0.005), erythrocyte sedimentation rate was= 57 mm/h (0-15), and N-terminus pro-B-type natriuretic peptide was= 679 ng/L (<125). Alkaline phosphatase, gamma-glutamyl transferase, lactate dehydrogenase, amylase, lipase, and renal function tests were normal. Chest X-ray showed no infiltration, and urinalysis revealed (+) leukocytes but (-) nitrites. Coronavirus disease-2019 (COVID-19) IgG was non-reactive (<0.05), and COVID-19 polymerase chain reaction (PCR) test was negative. During diagnostic work-up, the patient developed a fever as high as 41 °C, with a heart rate of 180 beats/min, raising clinical suspicion for possible urosepsis and infective endocarditis. As a result, treatment was adjusted to ceftriaxone, clindamycin, and vancomycin. ECG showed sinus tachycardia with PR interval of 140 ms, normal QRS duration and axis, normal QTc, and ST-T changes in V1 and V2 that were suggestive of Brugada pattern. Echocardiogram revealed no pathological findings. The cardiology team recommended aggressive fever control, avoiding sports, and provided a list of medications to avoid. Due to the history of seizures, lumbar puncture was planned, but the patient and family declined. The patient was evaluated by neurology and underwent diffusion and cranial magnetic resonance imaging (MRI), as well as electroencephalogram (EEG) monitoring. Cranial and diffusion MRI revealed no pathology, and the EEG was also normal. Abdominal US showed hepatosplenomegaly and a hypoechoic area in the upper pole of the spleen, measuring 9x7x8.5 cm, with no significant internal vascularization, but hypervascularity at the periphery, with peripheral millimetric air values, consistent with a splenic abscess. The diagnosis of a splenic abscess was confirmed by abdominal CT (Figure 1). Abdominal CT measurements indicated the liver size in the right lobe as 200 mm and the spleen as 138 mm. Minimal free fluid was noted in the right paracolic space and pelvis, with the deepest pocket measuring 2.5 cm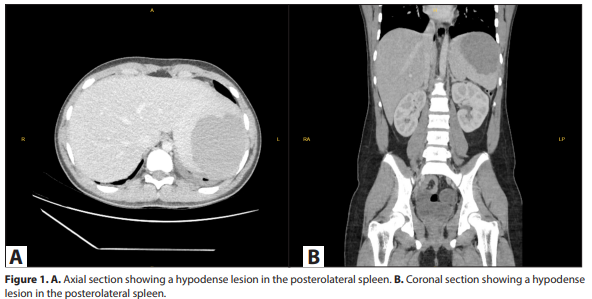
There was no growth in the patient’s urine culture, and Group A Streptococcus was not detected in the throat culture. Blood cultures taken during the febrile period revealed a gram-negative bacillus, leading to a diagnosis of gram-negative septicemia, and treatment was changed to meropenem, vancomycin, and amikacin. The abscess was drained percutaneously by interventional radiology, and a sample was sent for culture. The patient subsequently developed left-sided pleural effusion, and a thoracic tube was inserted. The serous fluid culture showed no growth, and tests for tuberculosis, including acid-fast bacilli and PCR, were negative. Smears for malignancy were also negative. Tests for viral agents (Epstein-Barr virus, cytomegalovirus, Herpes simplex virus-1, HIV), Toxoplasma gondii DNA PCR, autoantibodies, and peripheral blood smear revealed no abnormalities. Immunoglobulin levels, C3, C4, and nitroblue tetrazolium test results were normal. Flow cytometric analysis performed for lymphocyte subset evaluation was within normal litims. Tests for hydatid cyst, Rose Bengal, Brucella agglutination (with Coombs antiserum) were negative. Stool microscopy showed no leukocytes, erythrocytes, parasites, or ova, and stool culture revealed no pathogenic growth. Blood and abscess cultures grew Salmonella enterica spp. enterica. The isolate was susceptible to ampicillin, trimethoprim-sulfamethoxazole, ceftriaxone, ceftazidime, and ciprofloxacin. Vancomycin and amikacin were discontinued, and ciprofloxacin IV was initiated, while meropenem was continued. Ciprofloxacin was preferred so that oral therapy could be continued if discharge would be planned. Meropenem is continued for the first two days of ciprofloxacin, to let ciprofloxacin reach therapeutic levels. Hematological parameters showed progressive improvement, and by the fourth day of treatment, the WBC had reached 10.1 × 10⁹/L, with lymphocytes comprising 18.5% (ALC 1.88 × 10⁹/L) and PLT increasing to 220 × 10⁹/L. The patient diagnosed with BrS underwent serial ECGs and cardiology evaluations following ciprofloxacin administration, which revealed a normal cardiac axis, with PR interval, QRS duration, and QTc interval all within normal limits. A follow-up abdominal US after one month of ciprofloxacin treatment showed the splenic abscess had reduced in size to 48 x 38 mm. The patient, whose fever subsided, clinical condition improved, and abscess size reduced, was discharged to continue oral ciprofloxacin treatment. As part of the evaluation for underlying genetic conditions that may predispose the patient to invasive Salmonella infection, testing for Mendelian susceptibility to mycobacterial disease and sequencing of the IFNGR1 gene were conducted, revealing no pathogenic variants. Regular follow-up for BrS was recommended, the patient was advised to avoid high-risk activities, and a list of medications to avoid was provided. The patient’s ciprofloxacin treatment was completed over a total of 10 weeks, and at the eighth-month follow-up abdominal US, the abscess was found to have completely resolved
DISCUSSION
Splenic abscesses are rare in the pediatric population but carry significant risks of morbidity and mortality. While NTS typically causes self-limiting diarrhea in immunocompetent individuals, it can lead to invasive and focal suppurative disease in those with immunodeficiency. It is estimated that focal infections account for 7-12% of all NTS infections (10). In this case, a splenic abscess caused by S. enterica subsp. enterica is presented, with no immunosuppression detected in the patient. Patients with splenic abscesses may present with non-specific clinical symptoms such as high fever, abdominal pain, chills, cough, and dyspnea (1,2,4,11,12).However, these symptoms can be confused with many other infectious or inflammatory conditions. In this case, the patient’s presentation with fever and palpitations initially led to a cardiac-focused evaluation. However, US and CT were critical imaging methods that confirmed the diagnosis of a splenic abscess. In a study by Lee et al. On 16 splenic abscess cases collected over five years, left-sided pleural effusion was present in 50% of the patients (2). This rate varies between 22.3% and 41.5% in different studies (1,4,7). In our case, left-sided pleural effusion also developed, and it was drained via tube thoracostomy. Chiang et al. demonstrated positive blood cultures in 24% of cases (8). In the study by Lee et al., blood cultures were positive in 43.7% of cases, whereas abscess cultures yielded positive results in only 18.7% of cases (2). In a study by Chang et al. involving 67 splenic abscess cases over 19 years, blood culture positivity was reported in 71.8% of patients (4). In our case, the causative agent was detected in both the abscess and blood cultures. The spleen is an important part of the immune system, playing a vital role in defending against infections. However, splenectomy remains the traditional treatment method for splenic abscesses, and it is still standard against other comparable treatments (5). In recent years, there has been increased experience with percutaneous aspiration of splenic abscesses guided by CT and US. A meta-analysis comparing splenectomy and percutaneous drainage found a trend toward lower mortality and complication rates associated with percutaneous drainage (12). There is no established optimal duration of antibiotic therapy for splenic abscesses in clinical studies. For patients treated with percutaneous drainage, the duration of treatment should be adjusted based on clinical progress, particularly in response to the resolution of the abscess as assessed by imaging (5). In this case, splenectomy was not performed; instead, the abscess was drained percutaneously by interventional radiology, and when the infection was identified as S. enterica, the patient was switched to ciprofloxacin treatment. Fluoroquinolones constitute an important class of antibiotics owing to their high tissue penetration and potent bactericidal activity. Their notable in vitro efficacy against Salmonella species, alongside the convenience of oral administration, underpins their clinical preference. In a review by Kubin et al., the safety profile of ciprofloxacin in pediatric patients was reported to be comparable to that observed in adult populations (13). Moreover, a meta-analysis published in 2022 indicated that quinolone-associated musculoskeletal side effects tend to be transient and reversible, with no reported cases of severe musculoskeletal damage in children (14). After drainage and 10 weeks of ciprofloxacin therapy, the patient showed clinical improvement, and the splenic abscess resolved. Another significant finding in this case was the detection of a Brugada pattern. Effective fever control in patients with infections is critically important for those with BrS. This case highlights the clinical challenges posed by the co-occurrence of a rare splenic abscess and BrS in a pediatric patient. It also underscores the importance of recognizing atypical presentations of rare pathogens. The patient was thoroughly evaluated, and underlying immunosuppression was ruled out. The case is notable because the patient was immunocompetent and was successfully treated with antibiotics and percutaneous drainage, avoiding the need for splenectomy.